Archive for the
‘Mental Health Resources’ Category

Written by the clinical team at Lucent Recovery and Wellness in Austin, with statements from founder Chris Hudson, MA, LPC, LCDC.

In September, Travis County commissioners approved a Central Health budget that adds $54 million in new mental health and crisis funding, including 22 inpatient psychiatric beds and 10 psychiatric emergency bays (KUT). For Austin families, that is welcome news. More beds mean more people can be stabilized close to home.

It also means more families will meet the question that follows every hospital stay: what happens on the day after discharge? This guide is for the parent, spouse or sibling who is about to bring someone home, and wants a plan before that day arrives.

What happens after a psychiatric hospital stay?

After a psychiatric hospital stay, many adults need a step down in care, not a jump straight back to weekly therapy. In Austin, that usually means a partial hospitalization program (PHP) or an intensive outpatient program (IOP), with psychiatry, a written safety plan and a first appointment booked before discharge.

A hospital stay is short by design. Its job is safety and stabilization. The longer work of rebuilding sleep, routine, relationships and a sense of direction happens afterward, in the weeks when a person is home again and the structure of the unit is gone. Families who plan for that gap tend to feel far less lost inside it.

Why Travis County families are hearing about this now

Central Health, the county’s hospital district, put the problem plainly in August: Travis County has no dedicated psychiatric emergency department or comprehensive crisis center, so people in crisis too often land in emergency rooms, in jail or back on the street (Central Health).

The fiscal year 2027 budget answers part of that. According to Community Impact, $33.1 million goes to the new beds and emergency bays, and $16 million goes toward planning and launching a Mental Health Crisis Care Center. Officials described the psychiatric beds as the fastest-moving piece; the crisis center will take years. Central Health’s board chair called the funding a “down payment” (The Daily Texan).

Travis County fiscal year 2027 mental health investment: 22 new inpatient psychiatric beds, 10 psychiatric emergency bays and 54 million dollars in new crisis funding

Beds are one door into care. What families need just as much is the hallway on the other side of it: a clear next step, so that a hospital stay becomes the start of treatment rather than a pause before the next crisis.

Why the weeks after discharge deserve a plan

Researchers have studied the period after psychiatric discharge closely. A 2017 meta-analysis in JAMA Psychiatry, pooling 100 studies, found that the risk of suicide was highest in the first three months after discharge, and its authors concluded that people who have been hospitalized should be able to access longer-term care and assistance (Chung et al., 2017).

That finding is not meant to frighten anyone. It is the reason clinicians treat the move home as part of treatment, not the end of it. If you are ever worried about immediate safety, call or text 988, the Suicide and Crisis Lifeline, which is free, confidential and open around the clock, or call 911.

The levels of care between the hospital and weekly therapy

Most families know two settings: the hospital and the therapist’s office. Between them sits a set of steps that let someone keep the structure they need while sleeping at home.

Step-down diagram of mental health levels of care after a hospital stay: inpatient, partial hospitalization, intensive outpatient, then weekly therapy and psychiatry

Partial hospitalization (PHP)

Medicare describes partial hospitalization as a structured program of outpatient psychiatric services offered as an alternative to inpatient care (Medicare.gov). In practice, a person spends most of the day in treatment on weekdays and goes home at night. For someone leaving the hospital, PHP at Lucent keeps the day full and supervised while daily life starts to return.

Intensive outpatient (IOP)

An intensive outpatient program sits between once-weekly therapy and inpatient or partial hospitalization care, with group and individual therapy, education and medication management (Medicare.gov). It takes a few hours a day, several days a week, which leaves room for work, school or family. Read more about our intensive outpatient program in Austin.

Weekly therapy and psychiatry

Ongoing counseling and medication follow-up are where most people land for the long term. The aim of the earlier steps is to arrive here steady, with skills in hand, rather than all at once.

When home is not the right place yet

Sometimes the hardest part of discharge is the address. If going straight back to the family home is not workable, transitional housing in Austin can pair a stable place to live with daily treatment. For a fuller comparison of these settings, see our guide to levels of care in Austin.

A family checklist for discharge week

Hospital teams move quickly at discharge. These are the questions worth asking before the paperwork is signed.

Family checklist for the week of a psychiatric hospital discharge in Austin, from booking the first appointment to planning the first week

  • Book the first appointment before discharge. Leave with a date, a time and an address, not a phone number to call later.
  • Ask which level of care the team recommends next, and why. PHP, IOP or weekly therapy are different answers to different needs.
  • Get the medication list and the name of the next prescriber. Gaps in prescriptions are one of the most common problems in the first week.
  • Take the safety plan home in writing. Keep 988 saved in every phone in the house.
  • Sign releases of information. They let the hospital and the next provider talk directly, so no one starts from zero.
  • Choose one family point person. One person tracking appointments is calmer for everyone than four people texting.
  • Plan the shape of the days. Wake time, meals, transportation and who is home in the evenings matter more than they sound.

How Lucent works with families after a hospital stay

Lucent is a clinician-owned mental health practice in Austin offering PHP and IOP for adults. Every client takes part in the same core program of therapy and skills work. Around that core, the supports a person needs are opened one by one: coaching, help with work, fitness, housing. A master’s-level case manager holds the plan together and keeps the family informed with the client’s consent.

Families are part of the program, not visitors to it. Our page on what to expect for families explains how that works week to week.

Quote from Chris Hudson, founder of Lucent Recovery and Wellness: a hospital stay is built to get someone safe, not to teach them how to live the next ninety days

“A hospital stay is built to get someone safe. It is not built to teach them how to live the next ninety days. That part happens in the weeks after, and families should not have to work it out alone.”

Chris Hudson, MA, LPC, LCDC, founder of Lucent Recovery and Wellness

“Parents often ask me whether their son or daughter is ready to come home. I usually suggest a different question: what will the days look like? Structure is often what was missing, and it can be planned before discharge.”

Chris Hudson, MA, LPC, LCDC

Coming to Austin from elsewhere in Texas

Many families who call us live outside Travis County. Some choose Austin for a step-down program because it gives their loved one distance from the setting where things fell apart. If that is your situation, our article on traveling to Austin for mental health treatment covers the practical side, and our Austin mental health treatment page describes the program as a whole.

Frequently asked questions

Can someone go straight from the hospital into PHP or IOP?

Often, yes. When the hospital team and the outpatient program agree it is clinically appropriate, a person can begin PHP or IOP within days of discharge. Lucent completes an assessment first to confirm which level fits.

How soon after discharge should outpatient care begin?

As soon as it safely can. The best practice is to book the first appointment before discharge so that it happens within the first week, while the hospital’s recommendations are still fresh.

Does insurance cover partial hospitalization or intensive outpatient care?

Many plans cover both, and Medicare covers partial hospitalization and intensive outpatient services when criteria are met. Lucent is out of network with insurance plans but works with most of them. Our team can review benefits with you when you call.

What if my loved one does not want more treatment after the hospital?

That is common, and adults make their own decisions. Families can still get guidance on how to talk about next steps. Our article on types of interventions explains the options when someone is reluctant.

What should we do if things get worse at home?

If anyone is in immediate danger, call 911. For urgent emotional distress, call or text 988. For questions about stepping up care, our guide on knowing when a higher level of care is needed can help.

Planning a discharge in Austin?

If someone you love is in the hospital now, or has just come home, you can call Lucent at (512) 588-3899 during business hours or send us a message. A member of our clinical team will talk through what the hospital is recommending and whether PHP or IOP is the right next step.

Sources

  1. Central Health. “Central Health Focusing on Travis County’s Mental Health Crisis in Fiscal Year 2027 Budget.” August 28, 2026. centralhealth.net
  2. Aldridge, O. “Travis County approves Central Health budget, tax increase to support mental health initiatives.” KUT News, September 14, 2026. kut.org
  3. McLaren, J. “Central Health approves $54M for mental healthcare.” Community Impact, September 15, 2026. communityimpact.com
  4. Nevarez, A. “City approves new tax raise, investment in mental health initiatives.” The Daily Texan, September 17, 2026. thedailytexan.com
  5. Chung DT, Ryan CJ, Hadzi-Pavlovic D, Singh SP, Stanton C, Large MM. “Suicide Rates After Discharge From Psychiatric Facilities: A Systematic Review and Meta-analysis.” JAMA Psychiatry. 2017;74(7):694-702. PubMed
  6. Medicare.gov. “Mental health care (partial hospitalization).” medicare.gov
  7. Medicare.gov. “Mental health care (intensive outpatient program services).” medicare.gov
  8. 988 Suicide and Crisis Lifeline. 988lifeline.org

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

On July 27, 2026, the Substance Abuse and Mental Health Services Administration (SAMHSA) released the 2025 National Survey on Drug Use and Health, a national snapshot built from the self-reported responses of more than 60,000 people. One finding stands out for anyone who works in mental health care. Of the 54.6 million U.S. adults who had a mental illness in the past year, 33.9 percent, or 18.5 million people, also had a substance use disorder. Among the 18.2 million adults with a serious mental illness, the overlap was higher still: 42.9 percent, or 7.8 million people.

As a mental health treatment provider in Austin, we hear the stories behind those numbers from the families who contact us. A parent can’t tell whether a son’s sleepless, racing weeks are about stimulant use or the start of a mood disorder. A spouse is trying to understand whether a partner’s withdrawal is depression, drinking, or both. A family is watching a teenager disappear into a screen while their mood gets darker every month.

Many of these families eventually ask about an intervention. Most people picture a single scene from television: a living room, a circle of chairs, and a tearful confrontation. In reality, there are several types of interventions, and the one that fits depends a great deal on what your loved one is experiencing, especially their mental health.

We aren’t an intervention service. Our work begins when someone enters mental health treatment. But because mental health symptoms so often shape how an intervention should be planned, we want families to understand their options before they reach that point. In this guide, we’ll cover the main types of interventions, how mental health symptoms can change which approach makes sense, what the research says about different models, and where mental health treatment fits once a person is ready for care.

What an Intervention Is (and What It Isn’t)

An intervention is a planned, structured effort by the people who care about someone to help that person accept professional help. It doesn’t have to be an ambush, and in many cases it shouldn’t be.

Families usually encounter three broad models:

  • Invitational models (such as ARISE) bring the loved one into the process early. Nothing is planned behind their back.
  • Direct or confrontational models (often associated with the Johnson model) involve a prepared meeting where family members share how the person’s behavior has affected them and present a plan for treatment.
  • Family training models (such as CRAFT, the Community Reinforcement and Family Training approach) teach family members new ways to communicate, reinforce healthy behavior, and set boundaries over time, without one high-stakes meeting.

The research on these models is worth knowing. A randomized pilot study published in the Journal of Substance Abuse Treatment and archived by the National Institutes of Health summarized years of trials: family members using CRAFT engaged between 55 and 86 percent of treatment-refusing loved ones in care, while Al-Anon referral and the Johnson Institute intervention, the two approaches that historically dominated the field, showed lower engagement rates. Most of that research focused on substance use, but the underlying lesson carries over to mental health: preparation, respect, and ongoing family involvement tend to matter more than the intensity of a single conversation.

How Mental Health Symptoms Shape the Type of Intervention a Family Needs

This is the part of the conversation that often gets overlooked. An intervention isn’t only about getting someone to say yes. It’s about approaching them in a way their mind can actually take in at that moment. Mental health symptoms can change that dramatically.

Insight may be limited. In conditions like psychosis, mania, and some eating disorders, a person may not recognize that anything is wrong. Clinicians sometimes call this reduced insight. It isn’t stubbornness or denial in the usual sense. It’s part of the illness. Pressuring someone to “admit” a problem they can’t perceive usually backfires.

Fear and paranoia can escalate quickly. For someone who is already feeling watched or threatened, a surprise meeting with a room full of people can feel like confirmation of their fears. That’s one reason confrontational approaches are generally a poor fit when psychotic symptoms are present.

Depression affects energy, hope, and thinking. A person with severe depression may agree to help and then be unable to follow through on phone calls, forms, or appointments. The plan needs to account for that, with someone ready to help with the practical steps.

Suicide risk changes the priority. If a loved one is talking about not wanting to be alive, has made a plan, or has attempted before, safety comes before any other goal. That may mean an emergency evaluation rather than a family meeting.

Trauma can shape reactions. People with a trauma history may respond to confrontation, raised voices, or a sense of being cornered with shutdown, anger, or panic. Calm, predictable, and choice-based approaches tend to work better.

Substances can mask or mimic mental illness. Stimulants can look like mania. Alcohol withdrawal can look like an anxiety disorder. Cannabis can intensify psychotic symptoms in people who are vulnerable. When substance use and mental health overlap, it’s often impossible to know what’s driving what until a person is assessed in a stable setting.

Keeping these factors in mind can help families choose a safer, more realistic approach, and it’s a big part of why a mental health assessment is so often an early step.

Types of Interventions

Mental Health Interventions

A mental health intervention is often the least formal type. It’s usually for someone living with depression, anxiety, trauma-related symptoms, or another condition that’s slowly wearing down their work, school, relationships, or sense of self, but who isn’t in immediate danger.

The goal is rarely a dramatic commitment. More often, it’s an agreement to get a clinical assessment and an honest conversation about what level of support fits. Many families start with one trusted person saying something simple: “You haven’t seemed like yourself, and I’m worried about you. Would you be willing to talk to someone with me?”

SAMHSA offers practical guidance on how to talk to someone about getting help. For some people, the right next step is outpatient mental health counseling. For others whose symptoms are affecting daily functioning, a structured program such as a mental health intensive outpatient program (IOP) offers more support while they continue living at home.

High-Acuity Mental Health Interventions

High acuity means symptoms are severe, risk is elevated, or both. Examples include:

  • A first episode of psychosis, with hearing voices, beliefs that don’t match reality, or paranoia
  • Mania, with days of little sleep, reckless spending, or risky behavior
  • Severe depression with suicidal thoughts
  • A person who has stopped eating, sleeping, or caring for themselves

These situations put safety first. If someone is in immediate danger, call 911 or go to the nearest emergency room. For urgent emotional distress or suicidal thoughts, the 988 Suicide and Crisis Lifeline is available by call or text, 24 hours a day.

When the situation is serious but not an emergency, a high-acuity intervention usually calls for more planning than families expect. Calm, simple language, a trusted person in the room, and a care option that’s already identified tend to help far more than confrontation. Psychiatric evaluation is often an important part of stabilization, since medication may be part of treatment.

From the treatment side, people coming out of a crisis or hospital stay often need a step-down level of care rather than a sudden return to normal life. A partial hospitalization program (PHP) provides structured daily treatment, with a gradual step down to IOP as symptoms stabilize. At Lucent, psychiatric care is led by our Medical Director, Dr. Yahya Saeed, and you can learn more about our clinical team.

Substance Use Disorder (SUD) Interventions

SUD interventions are the type most people have heard of. They’re for someone whose alcohol or drug use is causing real harm and who has resisted or refused help.

The biggest change in this area over the past few decades has been a move away from shame. Families used to be told to wait for a loved one to “hit bottom.” The research on CRAFT and invitational models suggests families can influence change without waiting for a crisis.

SUD interventions also carry medical considerations. Stopping some substances abruptly, including alcohol and benzodiazepines, can be medically dangerous, so a plan often starts with an assessment for medically supervised withdrawal. It also needs a clear answer to the question, “Where does this person go if they say yes?”

From a mental health perspective, it’s worth asking what the substance may be doing for the person. Many people use alcohol or drugs to quiet anxiety, numb trauma, sleep, or escape depression. When that’s true, stopping the substance can bring those symptoms to the surface quickly, which is why mental health screening belongs in the plan from the start.

Co-Occurring SUD and High-Acuity Mental Health Interventions

This is where the 2025 NSDUH findings are most relevant. According to SAMHSA, among the 42.7 million adults with a past-year substance use disorder, 43.3 percent had a mental illness and 18.3 percent had a serious mental illness. For many families, the real question isn’t “Is this addiction or mental illness?” It’s “How do we get help for both?”

These are often the most complex situations to plan for. Psychiatric symptoms and substance use can intensify each other, and a person may be at higher risk during withdrawal or in the early days of treatment. Safety planning, medical assessment, and an understanding of both conditions all matter before anyone sits down to talk.

When a family needs structured, professional guidance through that process, organizations that specialize in SUD and high-acuity mental health interventions can help with preparation, choosing an intervention approach, and coordinating the transition into treatment. Intervention providers and treatment programs play different roles. Once a person is ready for care, a mental health treatment provider such as Lucent focuses on assessment, diagnosis, and ongoing treatment, with a plan that accounts for how the person’s mental health and substance use affect each other. Case management can help coordinate care across providers so that important details aren’t lost between one step and the next.

SAMHSA’s overview of co-occurring disorders explains why treating both conditions together matters.

Technology and Gaming Concerns

Technology concerns are one of the newer reasons families seek help, and they can be hard to read. Where is the line between a teenager who loves video games and one who is struggling? Between heavy social media use and something closer to dependence?

Clinicians generally focus on impact rather than hours alone. Warning signs include losing control over use, giving up activities and friendships, disrupted sleep, falling grades or work performance, intense irritability when devices are limited, and continuing despite clear consequences.

The mental health angle is especially important here. Problematic technology use frequently occurs alongside depression, anxiety, ADHD, and social isolation. For some young people, gaming or scrolling becomes the main way they manage feelings they don’t have words for yet. Taking the device away without addressing that can leave them with the distress and none of the coping.

Treatment appears to help. A systematic review and meta-analysis published October 21, 2025, in the International Journal of Environmental Research and Public Health examined psychological treatments for problematic use of the internet, video games, social media, and instant messaging among young people ages 10 to 21. Across nine studies with 744 participants, researchers found significant symptom reductions, with the strongest support for cognitive behavioral therapy (CBT), family therapy, and executive function training. The authors noted variation across studies and possible publication bias, so the findings are encouraging rather than conclusive.

For most families, the most useful “intervention” here is a family-level plan: agreed-upon limits, a curious conversation about what the technology is doing for the person emotionally, and a clinical evaluation for any mental health condition that may be underneath.

Gambling Interventions

Gambling disorder is a recognized mental health condition. It was reclassified alongside substance use disorders in the DSM-5 in 2013. Since the Supreme Court cleared the way for state-legalized sports betting in 2018, access has changed dramatically, with betting available on a phone at any hour.

Recent data suggests the change is showing up in clinical care. In June 2026, Epic Research published an analysis of electronic health records from more than 197 million U.S. adults between 2018 and early 2026. In states that legalized sports betting, the quarterly rate of diagnosed gambling disorder rose from 3.0 to 4.8 per 100,000 patients, roughly a 61 percent increase. In states without legal sports betting, the rate fell by about 29 percent. The largest proportional increase was among adults ages 18 to 29, whose rate more than doubled. The researchers noted the data shows an association, not proof of cause.

Gambling often overlaps with other concerns. A two-year study of more than 4,300 American adults, led by Joshua Grubbs at the University of New Mexico with researchers at Toronto Metropolitan University, found a meaningful link between sports betting and alcohol use: when one increased, the other tended to increase too.

Gambling interventions tend to involve a few distinct considerations:

  • Financial safety comes early. Protecting joint accounts, credit, and household finances is part of the plan.
  • Shame runs deep. Many people hide gambling debt for a long time. Confrontation can deepen the secrecy.
  • Emotional risk can rise quickly. Financial crisis and hopelessness can feed each other, so screening for depression and suicidal thoughts is important.
  • Other conditions need attention. Anxiety, depression, ADHD, and alcohol use often appear alongside problem gambling.

Eating Disorder Interventions

Eating disorders are among the most medically serious mental health conditions, and interventions here follow their own rules. Medical stability comes first, because restriction, bingeing, and purging can affect the heart, electrolytes, and other body systems. As with psychosis, a person may not recognize the seriousness of their illness, because the condition itself distorts how they see their body and behavior.

Families should avoid centering the conversation on weight, food, or appearance. Focus on what you’ve noticed about their health, mood, energy, and daily life, and on your care for them. A medical evaluation and a specialized eating disorder assessment are usually the first steps. You can read more about our approach on our eating disorder treatment page.
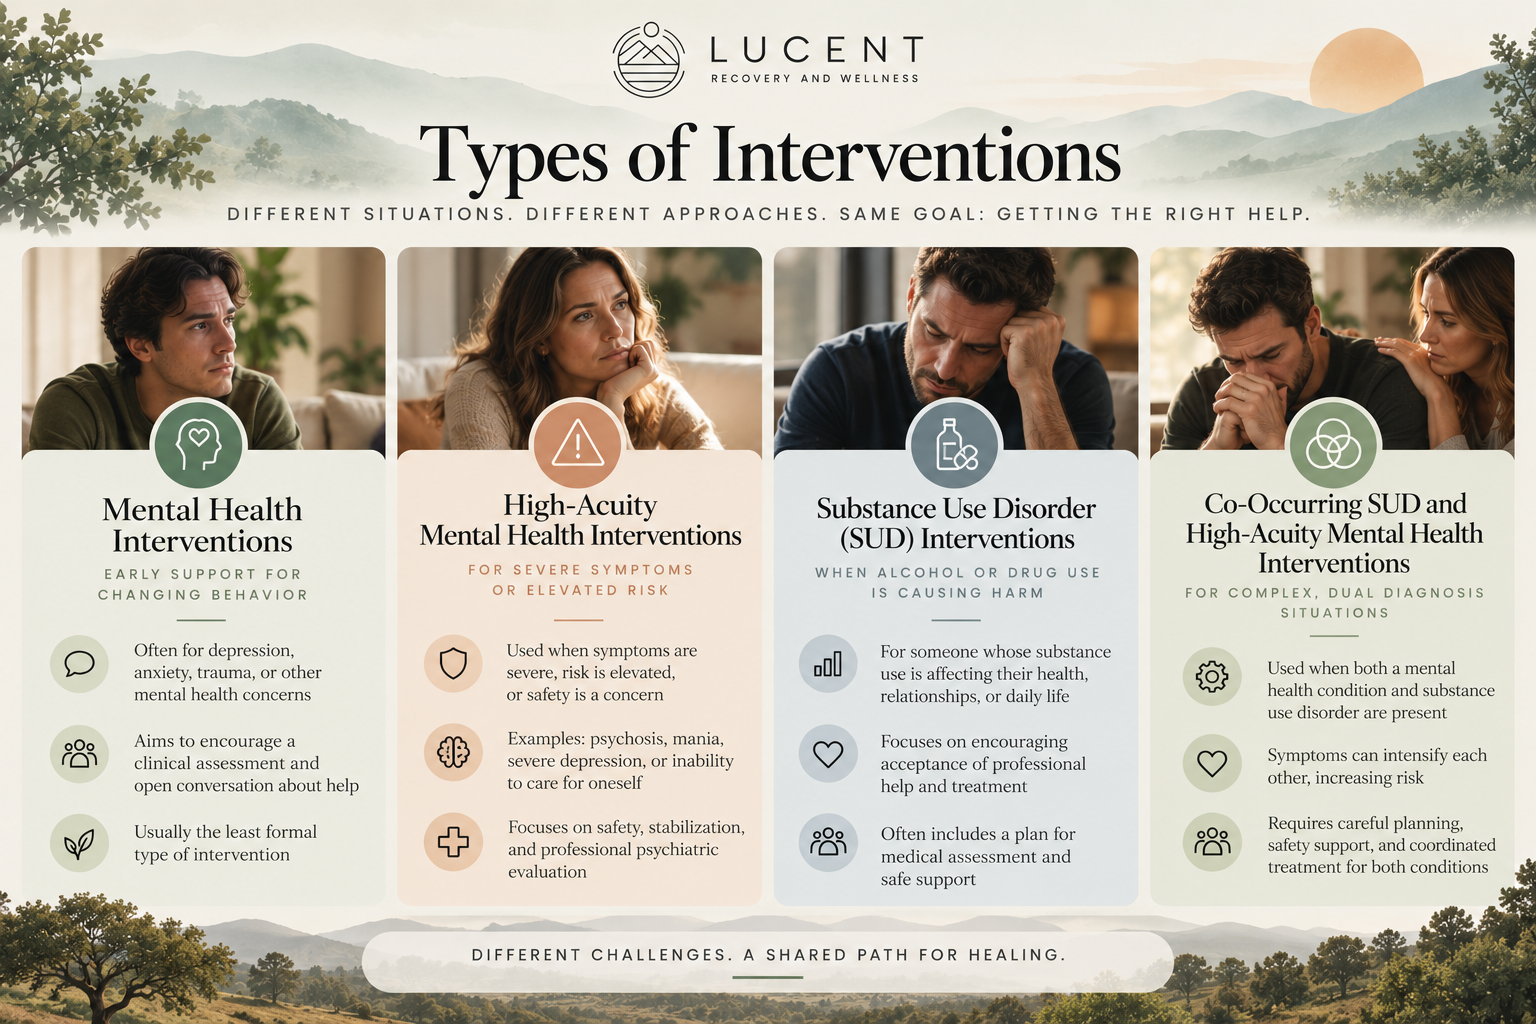
Lucent Recovery and Wellness infographic showing four types of interventions: mental health, high-acuity mental health, SUD, and co-occurring

Questions That Can Help Clarify Where to Start

It’s normal to feel unsure, especially when more than one concern is present. These questions can help:

  1. Is anyone in immediate danger? If so, call 911 or go to an emergency room.
  2. Are there signs of psychosis, mania, severe depression, or suicidal thinking? These point toward a safety-focused, psychiatrically informed approach.
  3. Is substance use involved, and could stopping be medically risky? Medical assessment belongs in the plan.
  4. Does your loved one seem able to recognize the problem? Limited insight often calls for a gentler, more patient approach.
  5. Has your loved one refused help repeatedly? That may be a sign the family would benefit from professional guidance, whether that’s family training, family therapy, or a professionally guided intervention.
  6. How is the family holding up? Exhausted or divided families often need support of their own.

Where Mental Health Treatment Fits

An intervention can open the door, but the longer work happens in treatment. For people whose symptoms are primarily or significantly related to mental health, that usually starts with a thorough assessment, followed by care matched to the level of need.

Depending on the person, that might mean outpatient counseling, an intensive outpatient program, or a partial hospitalization program for more structured daily support. Some people also benefit from practical supports during treatment, such as coaching or a structured living environment like transitional housing. The right combination depends on symptoms, safety, and the person’s goals.

Families are part of this, too. It helps to know what treatment involves and how to stay supportive without taking on the role of clinician. Our pages on what to expect for families and what to expect for clients walk through the early stages of care.

Practical Ways Families Can Prepare

Whatever type of intervention you’re considering, a few things consistently help:

  • Write down specific observations. “You haven’t left your room most days this month” lands differently than “You’re always shut away.”
  • Agree on one message. Mixed messages from family members make it easier for a struggling person to avoid the conversation.
  • Identify a next step in advance. Know where an assessment or appointment could happen before you talk.
  • Choose boundaries you’ll actually keep. Only state a boundary you’re prepared to follow through on.
  • Care for yourselves. Family members often carry anxiety, grief, and exhaustion. Their own support matters.

Common Myths About Interventions

Myth: A person has to want help for treatment to work. Many people start treatment with mixed feelings. Motivation often grows once someone feels safe and begins to feel better.

Myth: Interventions are always confrontational. Invitational and family training approaches are widely used, and research suggests they often engage loved ones as well as or better than confrontational ones.

Myth: If they say no, it failed. A no is often the beginning of a longer process. Families who keep communicating with care and consistency often see a loved one accept help later.

Myth: Mental health symptoms are just an excuse. Symptoms like reduced insight, paranoia, or depression-related exhaustion are real parts of an illness, and they affect how a person can respond to a hard conversation.

Frequently Asked Questions

How do I know if my loved one needs an intervention or just a conversation?

Start with a caring, private conversation if it’s safe. If you’ve tried several times without progress, the problem is getting worse, or there are safety concerns, it may be time to seek professional guidance on a more structured approach.

Does Lucent provide intervention services?

No. Lucent Recovery and Wellness is a mental health treatment provider. We can talk with families about treatment options and what care might look like, but we don’t provide professional interventionist services. Families who need help planning an intervention can work with a dedicated intervention provider, and treatment can begin once the person is ready.

Can an intervention be done for an adult who doesn’t live at home?

Yes, and most interventions involve adults. With adults, treatment participation is generally voluntary unless there is an imminent safety risk, which is why preparation and a respectful approach matter so much.

Should children or teens be included?

It depends on their age, maturity, and relationship with the person. Younger children usually shouldn’t be present for a difficult conversation. Older teens can sometimes share a meaningful perspective, but only with preparation and support.

What if my loved one has both a gaming problem and depression?

That combination is common. Addressing the technology use alone often misses what’s underneath. A clinical assessment can clarify whether depression, anxiety, ADHD, or another condition is involved so both can be treated together.

Is a surprise intervention ever appropriate?

Some families choose a direct approach when other efforts haven’t worked and the risks are serious. It should be carefully planned and led by someone experienced. It’s generally not a good fit for someone experiencing psychosis or paranoia, because surprise can heighten fear.

What should we do if the person gets angry and leaves?

Stay calm and don’t chase them. Let them know you love them and the offer of help still stands. Anger during a hard conversation is common, and many people return to it once the initial shock fades.

Do interventions work for gambling problems?

The same principles that help with substance use, including preparation, compassion, clear boundaries, and an identified next step, also apply to gambling. Gambling-related plans often add steps to protect household finances and screen for emotional crisis.

Conclusion

The 2025 NSDUH is a reminder of how often mental illness and substance use overlap: 18.5 million adults lived with both in the past year, and nearly 43 percent of adults with a serious mental illness also had a substance use disorder. Add rising gambling disorder diagnoses and growing concern about technology use, and it’s clear that families need more than one picture of what an intervention can look like.

The right type of intervention depends on the person, and mental health symptoms are often what tip the balance. Limited insight, paranoia, suicidal thinking, trauma, and depression can all change what’s safe and what’s realistic. A thoughtful approach takes those symptoms seriously, puts safety first, and connects the person with care that can address everything that’s going on.

Recovery rarely follows a straight line, and no single conversation solves everything. But with the right support, evidence-based treatment, and a family that’s cared for along the way, meaningful improvement in symptoms, relationships, and quality of life is possible.

When You’re Ready to Talk

If you’re concerned about the mental health of someone you love, or your own, you’re welcome to reach out. Our team can answer questions about mental health treatment, explain levels of care, and help you think through next steps. You can contact Lucent Recovery and Wellness or call 512-588-3899.

If you or someone you love is in immediate danger, call 911. For emotional distress or suicidal thoughts, call or text 988 to reach the 988 Suicide and Crisis Lifeline.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

Almost nobody wants group therapy at first.

People will agree to individual sessions, to psychiatry, to family work, to almost anything before they will agree to sit in a circle and say out loud what they have spent years not saying. The objection is nearly always some version of the same thing: I do not want strangers knowing this.

We understand the objection. We also see what happens about three weeks later, when the same person tells us group is the part they would not give up.

This article is about why that shift happens, what group work actually involves, and why it matters particularly when the thing you have been carrying involves food, your body, or the enormous private effort of managing both.

The thing that keeps this going is not really the food

Start with what the data says about company.

National Institute of Mental Health figures show that eating disorders almost never arrive alone. More than half of adults with anorexia nervosa, nearly 95 percent of those with bulimia nervosa, and roughly 79 percent of those with binge eating disorder met criteria for at least one other core psychiatric disorder. Anxiety disorders were the most common companion across all three.

Anxiety and shame are social conditions in a way that is easy to miss. They are made worse by concealment and they get better in the presence of people who do not flinch. That is not a slogan. It is the mechanism, and it is the reason a room full of other people is a strange but effective place to put someone who has been managing something in private.

The same NIMH data shows how much concealment is going on. Roughly a third of adults with anorexia nervosa and just over 43 percent of those with bulimia nervosa or binge eating disorder have ever sought treatment specifically for their eating disorder. Those figures come from the National Comorbidity Survey Replication, the most recent nationally representative diagnostic-interview data NIMH publishes, though the survey itself was fielded in the early 2000s.

Most people, in other words, never say it out loud to anyone at all.

What secrecy costs

We want to be careful here, because “just open up” is unhelpful advice and we are not offering it.

What we see clinically is that concealment has a compounding effect. The behaviour itself takes effort. Hiding the behaviour takes more. Managing the story you tell people about why you left dinner early, or why you cannot come to that thing, or why you have been tired, takes more again. By the time someone reaches us, a meaningful share of their available energy is going into maintenance rather than into living.

There is also the specific loneliness of believing you are the only one. People with disordered eating frequently describe their patterns as uniquely shameful, uniquely irrational, uniquely their own. The belief is usually wrong and almost always unshakeable from the inside. You cannot reason someone out of it, and individual therapy, for all its value, has a structural limitation here: your therapist can tell you that other people struggle this way, but your therapist is not other people.

What actually happens in group

Because the word “group” carries a lot of unhelpful associations, here is what it is not. It is not a circle of chairs where you are required to confess. It is not a support group where everyone takes turns describing their week. Nobody is going to make you speak.

What it is, in our programs, is structured clinical work with a facilitator and a purpose. Sessions have a focus. Skills get taught and then practised. Some groups are built around distress tolerance and emotion regulation, drawing on dialectical behavior therapy. Some are process groups where what happens between people in the room is the material. Some are psychoeducational.

A few things about the format do work that individual sessions structurally cannot.

You hear your own thinking in somebody else’s mouth. Someone describes a rule they follow, or a bargain they make with themselves, and you recognise it exactly. That recognition does more in ten seconds than months of being told you are not alone.

You get feedback that is not from a clinician. There is a particular weight to hearing something from a person who has no professional obligation to be kind to you, and who is clearly not saying it as technique.

You practise being seen. This is the underrated one. If the problem is partly that you have organised your life around not being perceived, then the intervention has to involve being perceived, in a setting where that is survivable.

You are useful to someone. People who have spent a long time as the problem in their family find something shifts when they say something in group that visibly helps another person.

We should be plain that these are clinical observations from our own programs rather than findings from a controlled trial. The broader evidence base for eating disorder treatment, summarised in a review by Allam and Attia of Columbia University published in Neurotherapeutics in October 2025, identifies eating disorder-focused cognitive behavioral therapy as consistently helpful for bulimia nervosa and binge eating disorder, and family-based treatment as effective for adolescents with anorexia nervosa and bulimia nervosa. What that review does not do is settle the question of format. We are telling you what we see, and labelling it as such.

The first session is the worst one

Everyone we have worked with agrees on this, so it is worth saying in advance.

The first session is uncomfortable. You will probably say very little. You will spend most of it deciding whether these people are safe and whether you have made a mistake. That is a normal and reasonable way to enter a room of strangers with something you have not told anyone.

The second is easier. By the third or fourth, most people have said something real, usually something smaller than the thing they are most afraid of, and discovered that the room absorbed it without incident.

We mention the timeline because the discomfort of the first session is the single most common reason people decide group is not for them, and it is the least representative data point available.

How group fits into the wider plan

Group is not the whole of treatment and it is not a substitute for individual work.

At Lucent, group sits at the centre of both our partial hospitalization program and our intensive outpatient program, supported by individual therapy, family involvement where that helps, and psychiatric care when it is part of the plan. Our master’s level case management team handles the logistics that make attendance possible, which matters more than it sounds when someone is trying to hold down a job at the same time.

Every therapist on our outpatient team holds a master’s degree and clinical licensure. Several of them chose this work specifically because of what they have seen groups do. If you would rather know who you are walking into a room with before you commit to anything, you can meet the team here.

If you are already working with a physician, a dietitian, or another provider, we coordinate with them rather than asking you to start over.

Frequently asked questions

Will I have to talk about food in front of people? Not unless you want to. You choose what you bring. Plenty of people spend their early sessions listening, and listening is participating.

What if I know someone in the group? Austin is smaller than it looks and this does happen. Tell us at assessment and we will place you accordingly. Nobody has to sit in a room with their neighbour or their colleague.

Is what I say confidential? Clinicians are bound by confidentiality. Other group members are asked to hold the same standard as a condition of participating, and it is taken seriously. We will not pretend the two are identical protections, because they are not, and that is worth knowing going in.

I am extremely introverted. Is this going to be awful? Introversion is not the obstacle people expect. Groups tend to be harder for those who arrive determined to manage everyone else’s impression of them, which is a different thing. Quiet people often do well.

Can I do individual therapy instead? You can, and for some people at some points that is the right call. What we would say is that if isolation and shame are part of what is keeping the pattern in place, individual work alone is treating around the problem rather than through it.

What if I try it and hate it? Then we talk about it and adjust. Level of care and format are working hypotheses, not sentences. Nobody is locked in.

How big are the groups? Small enough that you are not anonymous and there is room for everyone to speak. We keep clinician-to-client ratios low on purpose.

What we would want you to take from this

The instinct to keep this private makes complete sense. Disordered eating is frequently accompanied by real shame, and shame’s whole logic is that exposure will make things worse.

What we see, consistently, is the opposite. The thing that gets smaller is the thing that gets said in a room where nobody recoils. It happens faster than most people expect and it is difficult to arrange any other way.

You do not have to be ready to talk. You have to be willing to sit down.

Reach out

If any of this sounds like something you have been carrying alone, our team is glad to talk it through with no pressure. If you have been looking for eating disorder treatment in Austin, TX and are not sure where to start, an assessment is the place to begin.

For eating disorder support and referrals, the National Alliance for Eating Disorders runs a free helpline staffed by licensed therapists at 1-866-662-1235, Monday through Friday, 9:00 a.m. to 7:00 p.m. Eastern. If you or someone you love is in crisis, the 988 Suicide and Crisis Lifeline is available 24 hours a day by call or text at 988.

You can contact our team or call 512-588-3899.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

In November 2024 the National Center for Health Statistics published National Health Statistics Report 213, measuring symptoms of anxiety and depression among U.S. adults with the GAD-7 and PHQ-8. It found that 21.4 percent of adults had any symptoms of depression in a two-week period, up significantly from 2019.

More recently, the 2025 National Survey on Drug Use and Health, released by SAMHSA in July 2026, found that 54.6 million American adults experienced any mental illness in a single year, with nearly half receiving no treatment.

Screening instruments are useful and they have a specific limitation. A PHQ-8 or PHQ-9 asks about sleep, appetite, energy, concentration, and interest over the past two weeks. Someone whose spouse died five weeks ago will score high on all of it. So will someone in a depressive episode with no identifiable trigger. The instrument cannot tell them apart, and the treatment implications are not identical.

That distinction is one of the more common things adults ask us about, usually in the form: is this normal, or is something wrong with me?

What changed in how clinicians think about this

For a long time the diagnostic manuals contained what was called the bereavement exclusion. If someone’s symptoms followed the death of a loved one, a major depressive episode was generally not diagnosed within a set window afterward.

That exclusion was removed in DSM-5 and the current DSM-5-TR does not restore it. The change was controversial and it is worth understanding the reasoning, because it is frequently misreported as psychiatry deciding that grief is a disorder.

That is not what it says. The reasoning was closer to the opposite. Excluding bereaved people from a depression diagnosis meant that someone who developed a genuine depressive episode after a death was systematically denied recognition and treatment that an identical person without a recent loss would receive. Loss is one of the most powerful precipitants of depression, and the exclusion had the effect of withholding care from precisely the people at highest risk.

What the manual asks clinicians to do instead is exercise judgment: distinguish the expected response to a significant loss from a depressive episode, while recognizing that both can be present at once.

The DSM-5-TR also includes prolonged grief disorder, for grief that remains intense and disabling well past the point where most people’s begins to change, generally at least a year after the death for adults.

How we actually tell them apart

There is no single test. There are patterns, and they are reasonably consistent.

What is the relationship to the loss? Grief tends to be organized around the person or thing that was lost. Thoughts return to them. Sadness comes in waves, often triggered by reminders, with genuine stretches in between. Depression is more diffuse and more continuous, and it is frequently about the self rather than about the loss.

What does self-regard look like? This is one of the most useful distinctions. In grief, people generally do not think worse of themselves. In depression, worthlessness, excessive guilt, and a sense of being a burden are common. Someone saying “I miss her constantly” is describing something different from someone saying “everyone would be better off without me.”

Is pleasure fully gone or intermittently available? Grieving people typically retain the capacity for connection and occasional enjoyment, often with guilt attached to it. In a depressive episode, anhedonia is more complete and does not lift on a good day.

What is the trajectory over months? Grief changes shape. It does not disappear on a schedule, and it usually becomes less constant and more bearable. Symptoms that are flat or worsening at nine or twelve months are worth assessing rather than waiting out.

Are there safety concerns? Thoughts of death in grief are often about wanting to be with the person who died. In depression they more often involve wanting to end one’s own life. Both warrant attention, and the distinction matters clinically.

What people are actually grieving

One thing worth naming: a great deal of significant grief has nothing to do with a death.

Divorce. A diagnosis, yours or someone else’s. Estrangement from a family member. Infertility. A career that ended. A move away from a place and a community. Caring for a parent whose personality has been changed by illness, which is grief for someone still alive.

These losses frequently go unacknowledged because there is no ritual attached to them. Nobody brings food. There is no service, no leave, and no socially recognized period during which you are expected to be struggling.

That absence of recognition is part of why these losses so often produce something that looks less like grief and more like a slow depressive slide. There is no container for it, so it goes underground.

Why this comes up in Carrollton

We serve adults across the Dallas-Fort Worth metroplex, and Carrollton has a particular demographic reality worth noting.

It is an established, settled, internationally diverse city of roughly 130,000 people, with substantial Korean and Vietnamese communities among others, and a housing stock and population that skew toward long-term residents rather than recent arrivals.

Two things follow from that. The first is straightforward: settled populations include a lot of people in the stage of life where losses accumulate. Parents dying, marriages ending after decades, health changing, children moving away.

The second is that in many of the households we work with, grief is handled communally and privately at the same time. There is genuine support, often considerable, and there is also a strong expectation that a person will absorb what happened and continue. That combination works well for a great many people. Where it fails is when someone crosses from grief into a depressive episode, because the framework has no category for that. Continuing to struggle past the point where everyone expected recovery gets read as a failure of character or faith rather than as a medical development.

When treatment is the answer, and when it is not

Grief is not a disorder and most people do not need clinical treatment for it. What most people need is time, ritual, and other people. Support groups, faith communities, and family do more for ordinary grief than therapy usually does, and we would say so plainly rather than pathologizing something normal.

Treatment becomes appropriate in a few specific situations.

When a depressive episode has developed alongside the grief, particularly with worthlessness, pervasive anhedonia, or thoughts of self-harm. When grief remains intense and disabling well past a year, which may indicate prolonged grief disorder, for which specific treatments exist. When the loss reactivated an older trauma, which is common and frequently unexpected. When substance use has become the main coping strategy, which is one of the most common complications after a significant loss.

For most of these, weekly counseling is the right level, and it is where we would start.

A mental health intensive outpatient program becomes worth considering when a depressive episode has taken hold and is not shifting, when functioning has meaningfully deteriorated, or when grief and alcohol have grown into each other. Our program runs several hours a day, several days a week, over eight to twelve weeks, with partial hospitalization above it. Clients traveling from Carrollton generally stay in our transitional housing in Austin for the duration, and our case management team handles the practical side.

What actually helps while you are in it

Setting aside the diagnostic question, a few things reliably help people through significant loss, and a few reliably do not.

Other people who have had the same loss. This is the single most consistently useful thing, and it is why bereavement groups work as well as they do. Being understood without having to explain is a specific kind of relief that individual therapy does not replicate.

Ritual, including borrowed ritual. People who have no religious framework often improvise one, and it works anyway. An anniversary observance, a place you go, something you do on their birthday. The structure does something the sentiment alone does not.

Protecting sleep and reducing alcohol. Neither treats grief. Both substantially change how bad the following six months get. Alcohol in particular is the most common complication after a significant loss and the easiest to slide into unnoticed.

Being spared advice. Most people navigating loss report that the least helpful responses were the ones offering a frame for it. Presence outperforms interpretation.

Not deciding anything large for a while. Selling the house, changing jobs, ending or beginning a relationship. Not a rule, and worth a pause where circumstances allow.

What tends not to help: being told where you should be by now, comparisons to how someone else handled a similar loss, and the well-meant suggestion that you should be keeping busy. Distraction has its place and it is not the same as processing.

Frequently asked questions

How long is grief supposed to last? There is no correct duration, and anyone who gives you a number is wrong. What clinicians watch is change in shape rather than disappearance. Grief that is identical at eighteen months to what it was at two months is worth discussing with someone.

Is it wrong to take medication for grief? Medication does not treat grief and is not intended to. If a depressive episode has developed alongside it, medication may be appropriate for that, and it is a conversation with a prescriber. Grieving in itself is not a reason for a prescription.

I feel guilty when I enjoy something. Is that normal? Extremely, and it is one of the most common experiences people describe. It usually eases. If it hardens into a rule that you are not permitted to feel good, that is worth raising with a clinician.

What if I did not feel much when it happened? Delayed grief is real, and numbness is a common early response rather than an absence of feeling. Some people are hit hardest months later, often when everyone around them has moved on.

My loss was not a death. Does it count? Yes. Divorce, estrangement, illness, and the end of a career all produce genuine grief, and the lack of social ritual around them often makes them harder rather than easier.

Can a support group be enough? For a lot of people, yes, and for ordinary grief it is frequently better than individual therapy. Being among people who have had the same experience does something specific that a clinician cannot replicate.

What if I think it has become depression? Then it is worth an assessment. Grief and depression can coexist, and identifying the depressive piece does not diminish the loss or suggest you are grieving incorrectly.

The line matters because the response differs

About one in five American adults reports symptoms of depression in any given two-week window, and screening instruments cannot distinguish a bereaved person from someone in a depressive episode. That distinction is a clinical judgment, and it is worth making, because grief mostly needs time and people while depression frequently needs treatment.

If you are grieving, the most useful thing we can tell you is that struggling is not evidence that you are doing it wrong, and that there is no schedule you are behind on.

If something has shifted, and what began as missing someone has turned into thinking badly of yourself, sleeping poorly for months, and finding that nothing reaches you, that is a different situation and it responds to different help.

Working out which one you are in is a reasonable thing to ask for. Our team will talk it through honestly, verify your insurance, and tell you plainly whether our program for adults traveling from Carrollton is warranted or whether time, community, and a weekly clinician would serve you better. You can reach us through our contact page.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

Mental Health America’s State of Mental Health in America report ranks all fifty states and the District of Columbia across seventeen measures. On access to care, Texas ranks fifty-first out of fifty-one.

The ranking combines workforce availability, insurance coverage, and cost barriers. MHA reports that nearly one in five Texas adults with any mental illness had no health insurance. On a separate affordability measure, more than four in ten Texans experiencing frequent mental distress said they could not afford to see a doctor.

For people who have lived in Texas their whole lives, that ranking describes a familiar background condition. For the very large number of people who have moved to Collin County in the last decade, it is something else: a difference they encounter unexpectedly, usually at the worst possible moment.

The specific problem with moving

McKinney has been among the fastest-growing cities in the United States for years. A great many of its residents arrived recently, frequently for a job, frequently from another state.

Relocation is treated culturally as a logistical event. Find housing, transfer utilities, register the car, enroll the kids, learn the roads. Those things get planned.

What does not get planned is the replacement of everything that was holding a person up.

Your clinicians do not come with you. If you had a therapist you trusted, a psychiatrist who had spent years tuning a medication regimen, or a physician who knew your history, all of that stayed behind. Licensure is state-based, so in most cases a therapist in your previous state cannot simply keep seeing you across the line.

Your informal support disappears too, and it is harder to replace. The friend you called on a bad day. The sibling twenty minutes away. The neighbor who knew your kids. Those relationships took a decade to build and they are not replaced by a moving truck.

The people around you are new. New colleagues do not know your baseline. If you are struggling, nobody has a comparison point to notice against. Someone who has known you for fifteen years spots a change in three weeks. Someone who met you in March has no idea what you look like when you are well.

And in Texas specifically, re-establishing care is harder than where many people came from. Fewer providers per capita, longer waits, and a coverage landscape that surprises people arriving from states with different insurance markets.

The result is a specific and predictable window: six to eighteen months after a move, without a care team, without informal support, and without anyone nearby who would notice.

What often triggers it

Relocation is a stressor in its own right, and it frequently arrives bundled with others.

A job change, often a promotion with more responsibility. A spouse who moved for someone else’s career and is now isolated in a house all day in an unfamiliar place. Children struggling to settle, which parents absorb. Financial strain from the move itself. And in a lot of cases, distance from aging parents, which produces a low, continuous anxiety that has nowhere to go.

There is also a quieter one that people rarely name. Many moves are undertaken with genuine optimism. A better school district, a bigger house, a real opportunity. When someone is not happy afterward, the optimism becomes a reason not to say anything. You cannot easily complain about a life you chose and other people envy.

That silence is often the most damaging part.

What to actually do, in order

Rebuilding a support structure is a project. Treating it as one helps.

Establish primary care before you need it. This is the single most useful step and almost nobody does it proactively. A primary care physician can assess, prescribe, rule out physical contributors, and refer. In a state with a thin behavioral health workforce, having a physician already in place shortens every subsequent step considerably.

Get your records transferred. Ask your previous providers for your history, including medication trials and what did and did not work. Arriving at a new prescriber with an accurate record can save months of retrying things you already know failed.

Ask your previous therapist for a referral, not just a goodbye. Clinicians have networks and many will make an effort to find someone appropriate in your new city.

Check whether your plan changed. People frequently assume their coverage moved with them. Employer plans often have different networks in different regions.

Rebuild the informal layer deliberately. This feels artificial and it works anyway. Recurring, low-effort commitments are what actually produce friendships in adulthood. A weekly class, a league, a volunteer shift, a standing arrangement. Not because it will replace what you had, but because the thing you had also started somewhere.

Keep one long-distance relationship active on purpose. Whoever knew you best before the move is a genuinely valuable early warning system, and a scheduled call is more reliable than good intentions.

When it has gone past adjustment

There is a difference between the ordinary difficulty of relocating and a clinical condition, and it is worth being specific about it.

Adjustment difficulty tends to improve as things become familiar, and it lifts noticeably during good stretches. Trajectory matters more than any single symptom.

Markers that something else is happening: symptoms persisting well past the first year. Anhedonia, where things that used to reliably produce pleasure now produce nothing. Early morning waking. Persistent guilt or a sense of being a burden. Anxiety present on weekends and vacations, not only tied to work. Alcohol having become a structural part of the evening.

At that point weekly counseling is the sensible starting point, and it helps a great many people.

Where a mental health intensive outpatient program becomes worth considering is when the pattern predates the move, when weekly care has plateaued, or when the isolation and the symptoms have started reinforcing each other. Our program runs several hours a day, several days a week, over eight to twelve weeks, with partial hospitalization above it for people who need more structure.

There is one thing worth naming for people in this specific situation. A significant part of what an intensive program provides is a peer community. For someone who has been isolated since a move, being known by a group of people over several weeks does clinical work that is difficult to arrange any other way. Clients traveling from McKinney generally stay in our transitional housing in Austin for the duration, which supplies that community alongside a consistent schedule. We serve adults across the Dallas-Fort Worth metroplex.

Discharge planning matters more than usual here, because you are returning to a place where your support network is still thin. Our case management team builds the North Texas connections before you leave rather than handing you a list on the last day.

The trailing spouse problem deserves its own section

In a substantial share of relocations, one adult moved for a job and the other moved for the first adult. The second person’s situation is consistently underweighted, including by themselves.

The pattern is fairly consistent. The person who relocated for work arrives with a ready-made structure: colleagues, a schedule, a reason to be in the building, and immediate social contact whether they want it or not. Their spouse arrives with a house and a list.

Then the asymmetry compounds. One person is meeting twenty new people a week. The other may go days speaking only to their own children. One has visible progress to report at dinner. The other has unpacked boxes.

And there is usually a reason not to raise it. The move was for the family. It was the right decision financially. Complaining feels like undermining something that everyone agreed to, particularly when the other person is working hard to justify it.

What we would say to both people in that arrangement:

For the person who moved for work: their isolation is not a temporary adjustment phase that will resolve on its own, and it is not solved by suggesting they join something. Treat rebuilding their social structure as a shared project with actual time allocated to it, the way the job search or the house search got time allocated.

For the trailing spouse: the fact that you agreed to the move does not remove your standing to struggle with it. Those are separate questions. If this has been going on past a year and is not improving, it is worth an assessment in its own right rather than as a footnote to someone else’s transition.

And if you are reading this within your first few months here, the most useful thing you can do is the thing that feels least urgent: get a primary care physician on the books now, while nothing is wrong. In a state with this much pressure on the behavioral health workforce, already having that relationship is worth more than any amount of research you can do later.

Frequently asked questions

Can I keep seeing my therapist from my previous state by video? Usually not on an ongoing basis. Licensure is generally state-based, and most clinicians can only treat clients located in states where they are licensed. Some hold multiple licenses, so it is worth asking directly.

How long should adjusting to a move take? There is no fixed number, and a rough guide is that most people feel meaningfully more settled within a year. Symptoms that are the same or worse at eighteen months are worth assessing rather than waiting out.

My spouse moved for my job and is struggling. What can I do? Take it seriously as its own situation rather than a temporary mood. The trailing spouse in a relocation frequently carries the heaviest isolation and the least acknowledgment of it. Support, and treatment if warranted, should be theirs rather than an extension of yours.

Is it worth starting treatment if I might move again? Yes. Short courses of treatment are worthwhile, and a good clinician will help you plan for portability, including documentation you can take with you.

Does homesickness count as a real problem? Grief over a place, a community, and a version of your life is real and it does not require a diagnosis to be worth addressing. It also sometimes develops into a depressive episode, which is worth catching.

What if I do not have anyone here to help with logistics? Say so on the first call. Our case management team handles insurance, authorization, and coordination, and for people without local support that is a substantial part of what we provide.

How do I find a physician in a state where access is this thin? Start with your insurer’s directory, then call rather than relying on online availability, and ask specifically whether they are accepting new patients. Concierge and direct primary care practices are an option in Collin County if cost allows.

Fifty-first is a harder landing if you did not grow up here

Texas ranks last in the country on access to mental health care, driven largely by coverage and workforce rather than by an absence of good clinicians. For someone who has just arrived, without a care team, without local relationships, and without anyone nearby who would notice a change, that ranking stops being a statistic and becomes a set of unreturned phone calls.

None of that means good care is unavailable. It means finding it takes more deliberate effort than it should, and that starting before you urgently need it is worth a great deal.

If you moved recently and the last year has been harder than you expected to admit, that is worth a conversation. Our team will assess honestly, verify your insurance, and tell you plainly whether our program for adults traveling from McKinney is the right level of care or whether something local would serve you better. You can reach us through our contact page.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

The 2025 National Survey on Drug Use and Health, released by SAMHSA on July 27, 2026, found that 54.6 million American adults experienced any mental illness in the past year. Of those, 49.1 percent received no treatment at all.

Nearly half. And among adults with a serious mental illness, defined as producing substantial impairment in major life activities, roughly one in three received nothing.

Those numbers get quoted often as evidence of an access crisis, which they partly are. But a large share of the people inside them are not stuck on a waitlist. They have never made the first call, and a meaningful reason is that they have no idea what happens if they do.

That is a solvable problem, and it is what this article is for. No persuasion, no case for why you should get treatment. Just an accurate description of the process for someone who has never spoken to a mental health professional.

Why not knowing is such an effective barrier

People will tolerate a great deal of discomfort rather than enter a situation they cannot picture.

Most of what people do know about mental health treatment comes from film and television, where it is either a leather couch and a beard, or a locked ward. Neither resembles ordinary outpatient care, and both are alarming in different ways.

The specific fears we hear most often, in roughly this order:

That they will be committed against their will. That they will be put on medication immediately. That something will go on a permanent record. That their employer will find out. That they will be told their problems are not serious enough. That they will be told their problems are much more serious than they thought. That they will not know what to say.

Every one of those is answerable, and most of the answers are reassuring in a boring way.

What actually happens, step by step

The first call is short. Fifteen to twenty minutes with someone whose job is to understand your situation well enough to route it. You are asked what is going on, roughly how long it has been going on, what you have tried, and what your practical constraints are. You are not obligated to tell a stranger your full history on a first call, and nothing is scheduled unless you say so.

Insurance verification is separate and administrative. You provide plan details, we check what your benefits cover, and you get a specific answer back, usually within a day or two. This happens before any commitment.

The clinical assessment is the long conversation. An hour or more with a clinician, covering symptoms, history, sleep, substance use, medications, family, work, safety, and what you want to be different. It is not a test. There is no way to fail it, and there is no wrong answer.

You get a recommendation, and it is frequently for less than you expected. Assessment ends with a level of care recommendation. For a large share of people that is weekly counseling, which is where most treatment should start. Being told you do not need intensive care is a normal outcome, not a rejection.

If more structure is warranted, that gets explained. A mental health intensive outpatient program provides several hours of structured clinical work several days a week over eight to twelve weeks. Partial hospitalization is more intensive again. Nobody is enrolled without understanding what they are agreeing to.

You can stop at any point. Voluntary treatment is voluntary at every stage, including after an assessment.

Answering the fears directly

Will I be committed? Involuntary commitment in Texas requires specific legal criteria centered on imminent danger, and it involves a legal process, not a clinician’s preference. It is rare, and it is not what happens when someone calls a program to ask about depression. If you are worried about this, ask about it on the first call. It is a reasonable question and you will get a straight answer.

Will I be put on medication? Not automatically, and not by us. We are not a prescribing practice. Medication decisions belong to you and a prescribing clinician, and psychotherapy is effective on its own for a substantial number of people with depression and anxiety disorders.

Will this go on a permanent record? Your treatment creates a medical record, protected like any other. It is not a public document, it does not appear on a background check, and it is not shared with an employer without your written authorization. Substance use treatment records carry additional federal protections beyond standard health privacy rules.

Will my employer find out? Not from us. If you need documentation for a leave process, our case management team prepares only what the process requires, which is certification of a qualifying condition and a schedule, not your diagnosis or your session content.

What if my problem is not serious enough? Then a clinician will tell you what would help, which might be weekly therapy or might be something else entirely. Nobody is going to be irritated that you called. In our experience the people who worry about wasting a clinician’s time are almost never the people who are.

What if I do not know what to say? You do not have to arrive organized. “I do not know how to explain this, but something has been wrong for about two years” is a completely sufficient opening. Structuring the conversation is the clinician’s job.

The Grand Prairie context

We serve adults across the Dallas-Fort Worth metroplex, and there is a reason a first-timer’s guide is the right article for this city.

Grand Prairie sits between Dallas and Fort Worth with a working population employed heavily in aviation, manufacturing, logistics, and services. Many households run on shift schedules and hourly work. It is a young, diverse city where a substantial number of families are the first generation to have employer health coverage at all.

In that context, mental health care is frequently not something a person has decided against. It is something that was never a visible option. Nobody in the household has done it. No one at work talks about it. The nearest reference point is a relative who was described for years as having a hard time.

When care has never been modeled, the barrier is not resistance. It is that the entire process is unfamiliar, and unfamiliar things get postponed indefinitely in favor of endurance, which is a skill most people in this situation already have in abundance.

Where to start if we are not the right fit

We would rather be useful than only be an option, so here is a fair map.

A primary care physician is often the best first step and the most schedulable clinician in most people’s lives. They can assess, rule out physical contributors like thyroid problems or sleep apnea, prescribe, and refer.

An employee assistance program, if your employer has one, typically offers a few free confidential sessions. Use is not reported to your employer.

Community mental health services serve people regardless of ability to pay. Expect a wait, and get on the list anyway.

Weekly outpatient therapy with sliding-scale or training-clinic options, which exist and serve people well.

The 988 Suicide and Crisis Lifeline, available by call or text at any hour, with no insurance, appointment, or time off work required.

What to say on the first call if you do not know how to start

The most common thing that stops a first call is not fear of treatment. It is not having a sentence ready. So here are several that work, and any of them is enough.

“I do not really know how to describe this, but something has been off for about two years.”

“I think I might be depressed but I am not sure, and I do not know what the next step is.”

“My drinking has changed and I want to talk to someone about it.”

“My wife thinks I should call. I am not sure I agree, but I said I would.”

“I have never done anything like this and I do not know what I am asking for.”

That last one is completely sufficient. A significant share of our first calls open with some version of it.

A few things it helps to have nearby, though none are required: the name of your insurance plan, a rough sense of how long this has been going on, and any medications you take. If you do not have them, we will work with what you have.

And one practical note. If you can only take a call at certain hours because of a work schedule, say that in your first message or voicemail. It is an ordinary request, it is not a complication, and it is far better than a series of missed calls that ends in nobody calling back.

It is also fine to call and ask nothing more than what the process involves, without describing your situation at all. Plenty of people do exactly that, hang up, and call back weeks later once they have had time to think. Nobody is tracking you, and there is no cost to gathering information first.

Frequently asked questions

Do I need a referral from a doctor? No. You can contact us directly and schedule an assessment.

How much does an assessment cost? Our initial conversation about level of care and insurance carries no charge. We verify your benefits and explain any cost before you commit to anything.

What if I have no insurance? Say so on the first call and we will give you real self-pay figures rather than routing you toward a number you cannot use. If it is not workable, we will point you toward options that might be.

Can I bring someone with me? To an assessment, frequently yes, and for people who have never done this it often helps. Our page for families covers how family involvement works.

How long until I feel different? It varies genuinely, and we would be skeptical of anyone giving you a firm number. We use standardized symptom measures throughout treatment and review them with you, so progress is something observed rather than guessed at.

What if I start and decide it is not for me? You can stop. What we would ask is that you tell us why, because sometimes the issue is a fixable fit problem rather than treatment itself.

Is it too late if this has been going on for twenty years? No. Long-standing conditions generally take longer to shift and remain treatable. We have worked with people who spent decades assuming this was simply their personality.

Half of people get nothing, and not all of them chose that

Nearly half of American adults with a mental illness received no treatment last year. Some are on waitlists, some cannot afford it, and some are working hours that make care impossible to schedule.

But a real share have simply never made a call they cannot picture the other end of. That is a much smaller obstacle than it feels like from the inside, and it is the one this article can actually remove.

A first conversation commits you to nothing. It costs twenty minutes, and it usually ends with a clearer picture than you had going in, sometimes including the news that what you need is smaller and more manageable than you feared.

If you have been circling this, we would be glad to talk. Our team will answer questions about our program for adults traveling from Grand Prairie, verify your insurance, and tell you plainly if something else would serve you better. You can reach us through our contact page.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

In April 2025 the National Center for Health Statistics published Data Brief 527, using PHQ-9 screening data from the National Health and Nutrition Examination Survey collected between August 2021 and August 2023. It found that 13.1 percent of people age 12 and older had depression in a two-week period, and that prevalence was higher among women, 16 percent, than among men, 10.1 percent.

The finding we keep returning to is a different one. Among people who met the threshold for depression, 87.9 percent reported at least some difficulty with work, home, or social activities as a result.

Nearly nine in ten. Which means depression is almost never a purely internal event. It has a footprint in a household, and in households with children the footprint is usually absorbed rather than addressed.

We see the result of that absorption regularly, and a disproportionate share of those calls come from Frisco.

The Frisco version

Frisco is one of the fastest-growing cities in the country, and it grew by attracting families. Young households, new neighborhoods, a school district that people relocate specifically to enroll in, and a youth sports infrastructure that shapes the weekly calendar of a very large number of families.

The adults who call us from Frisco are frequently in their thirties and forties with school-age children. They have organized their lives with real competence around their kids’ needs. Practices, tournaments, appointments, tutoring, activities. The calendar is full and it is full of things that matter.

And somewhere in that structure, their own care simply has no slot.

Not because they do not believe in it. Most of them have arranged therapy for a child, or supported a spouse through something, or read extensively about a condition they suspect they have. The knowledge is there. What is missing is a place to put their own treatment inside a week that is already fully allocated to other people.

This is not the same barrier as stigma or cost. It is a scheduling and priority problem, and it responds to different arguments.

How it usually presents

A recognizable cluster shows up in these assessments.

Depletion that gets attributed entirely to logistics. Being tired makes obvious sense when you drove ninety minutes to a tournament on Saturday. What gets missed is that the exhaustion is disproportionate to the activity and does not resolve with a quiet weekend.

Irritability with the children, followed by guilt. This is often the symptom people are most ashamed of and least willing to raise. It is also one of the most common presentations of depression in parents, and it is one of the more reliable signals that something has moved past ordinary strain.

Loss of everything optional. Friendships, hobbies, and any activity without a productive justification went first, frequently years ago. Because it happened gradually and for defensible reasons, nobody registered it as loss.

Anxiety that presents as vigilance. Constant scanning, difficulty being still, an inability to sit through a movie. In a parenting context this reads as conscientiousness, which makes it nearly invisible.

Marital distance rather than conflict. Two people running parallel logistics operations who have not had a real conversation in eight months.

Alcohol as a structural part of the evening. Socially normal, quantitatively unremarkable, and quietly load-bearing.

The argument that actually lands

We have learned not to lead with self-care language, because it tends to bounce off parents who have consciously decided their own needs come second.

The more useful framing is the one the NCHS finding points at. Depression interferes with functioning in the home for nearly nine out of ten people who have it. That interference is already happening. It is not a hypothetical cost of prioritizing yourself. It is a present cost of not doing so, and it is being paid by the household.

Which means the choice is not between your children’s needs and your own. It is between treating something that is affecting your household now and continuing to absorb it.

Parents generally find that a more persuasive frame, and we think it is also the more accurate one.

There is a second point worth making plainly. Children of parents with untreated depression are at elevated risk themselves, through both genetic and environmental pathways, and the NCHS prevalence data shows depression is already common in the age groups most likely to be raising them. Treating a parent is a well-supported intervention for the family, not a diversion of resources away from it.

What treatment can look like inside a full life

Most people do not need intensive care. Weekly counseling is the right starting point for a large number of situations, and it is the most schedulable option available. If you have never tried it, that is where to begin.

Where we come in is further along the line. A mental health intensive outpatient program provides several hours of structured clinical work several days a week over eight to twelve weeks. It suits people whose pattern has been running for years, who have plateaued in weekly therapy, or whose mood and drinking have grown into each other.

We will be straightforward about the tension for parents. An IOP does not fit around a school pickup schedule. Most of our clients traveling from North Texas step back from their usual routine for the duration, stay in our transitional housing in Austin, and arrange coverage at home.

For a parent, that is a significant thing to ask, and we would not minimize it. The honest counterargument is that eight to twelve weeks is a defined period, and that many of the parents who do it have already spent three to five years managing an untreated condition while running a household. The comparison is not between treatment and normal life. It is between a bounded interruption and an open-ended one.

Our case management team works on the logistics, including leave documentation, and our page for families covers how we involve spouses and, where appropriate, children across distance. We serve adults throughout the Dallas-Fort Worth metroplex.

What to tell the children

Parents ask this constantly and the answer depends heavily on age, so here are the principles rather than a script.

Say something. Children notice more than parents expect, and in the absence of an explanation they generate one, which is usually that they are somehow responsible.

Keep it simple and true. That you have not been feeling well, that you are getting help from people who know how to help with this, and that it is not their fault and not their job to fix.

Give them a timeline if you have one. Uncertainty is harder on children than difficulty.

Do not make them a confidant. The line between being honest with a child and asking a child to carry an adult’s distress matters, and it is easy to cross when you are depleted.

Let them see the getting better part. Watching a parent seek help and improve is a genuinely useful thing for a child to witness. It teaches something that no conversation about mental health can teach as effectively.

What the first bounded step looks like

Parents deferring care often need the entry point to be smaller than an eight to twelve week program, so here is the smallest useful version.

Book a primary care appointment. One visit. A physician can screen for depression and anxiety, rule out thyroid problems, anemia, and sleep apnea, prescribe if appropriate, and refer. It is the most schedulable clinical appointment in most parents’ lives and it moves things forward more than reading about it does.

Ask for one thing to be taken off you for six weeks. Not permanently. A specific recurring obligation, handed to a spouse, a relative, or a paid arrangement. Parents in this situation are usually carrying several things that are transferable and have never been examined.

Put a sleep floor in place. A consistent wake time and a protected window, treated as non-negotiable rather than aspirational. Sleep is the lever with the largest downstream effect and the one most easily lost in a family schedule.

Tell one adult the true version. Not the summary you give at pickup. One person who gets the accurate account. The difference between nobody knowing and one person knowing is disproportionately large.

Set a review date. Six weeks out, written down. If nothing has changed by then, that is information, and it is the point at which a fuller assessment stops being optional.

None of that is treatment. All of it is achievable inside a full week, and it either helps or it tells you clearly that the problem is larger than logistics.

One more thing. If a spouse or a friend gave you this article, that is worth treating as information rather than as pressure. People generally do not send something like this to someone they are not already worried about, and they have usually been worried for a while before sending it.

Frequently asked questions

Is what I have depression or just exhaustion from parenting? Both exist and they overlap heavily. A rough distinguisher: exhaustion improves meaningfully with rest and support, and depression largely does not. If a genuinely restful stretch changed nothing, that is worth taking seriously.

Can I do a program without leaving my kids? Weekly therapy, yes. Intensive programming requires coverage at home for the duration. We will talk through what is realistic in your situation rather than encouraging a plan that will collapse in week three.

What if my spouse does not think this is necessary? That happens, and it is worth addressing rather than working around. Sometimes a spouse is minimizing. Sometimes they are genuinely unaware of the internal experience because the external functioning held. A family session frequently helps more than an argument.

Will treatment affect custody if I am divorced or separated? Seeking voluntary mental health treatment is generally viewed as responsible rather than disqualifying, though family law is jurisdiction-specific and we are not attorneys. If this is a live concern, it is worth a conversation with a family law attorney before you decide.

Does postpartum depression fall under this? Perinatal mood and anxiety disorders are common, treatable, and frequently missed well past the first year. If your symptoms began around a pregnancy or birth, say so during assessment because it changes the clinical picture.

Is medication compatible with breastfeeding? Many options are, and that decision belongs to you and a prescriber who can weigh the specifics. It is not a reason to avoid the conversation.

What happens after the program? Discharge planning begins early and covers ongoing providers in North Texas, a realistic first month back inside a family schedule, and whether stepping down through continued counseling or recovery coaching makes sense first.

The cost is already being paid

Nearly 88 percent of people with depression report that it interferes with work, home, or social activities. If you are a parent with an untreated mood or anxiety condition, that interference is not a future risk you are avoiding by deferring care. It is a present cost, and your household is already covering it.

That is not a reason for guilt, which parents in this situation have in abundant supply already. It is a reason to reconsider the arithmetic. Treating a parent is one of the more effective things a family can do for itself.

Depression and anxiety are treatable, and the outlook for people who get appropriate care is genuinely good, though no one can promise a particular result for a particular person.

If you have been putting this off, we would be glad to talk it through. Our team will assess honestly, verify your insurance, and tell you plainly whether our program for adults traveling from Frisco fits your life right now or whether something closer to home would serve you better. You can reach us through our contact page.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

When SAMHSA released the 2025 National Survey on Drug Use and Health on July 27, 2026, it asked adults who knew they needed treatment and had not received it to say why.

The most common answer, given by 82.5 percent of them, was that they thought they should be able to handle it on their own. That answer outranked cost, insurance, availability, and timing by a wide margin.

The same survey found that among the 54.6 million American adults who experienced any mental illness in a single year, 49.1 percent received no treatment at all.

Public health messaging tends to treat that self-reliance answer as stigma to be corrected. We think it deserves more respect than that, and more precision. For a great many people, and particularly in households where mental health has never been discussed as a medical matter, self-reliance is not ignorance. It is a value, a family history, and often a survival strategy that worked.

The version we hear from Irving

We serve adults across the Dallas-Fort Worth metroplex, and Irving produces a distinct pattern.

It is one of the most internationally diverse cities in the United States. A city of roughly a quarter million people, with a major corporate presence in Las Colinas, an airport on its border, and residents from a very wide range of countries and first languages. A substantial number of the adults who call us from Irving are either immigrants themselves or the adult children of immigrants.

The pattern goes something like this. Someone in their thirties or forties, professionally successful, calls about symptoms they have had for years. They are articulate about what is happening. They have often read about it thoroughly. And somewhere in the first ten minutes, they say a version of: my parents would not understand this, or, we do not really talk about this in my family.

Sometimes it is more specific. That there is no word for this in their first language that does not also imply something shameful. That a relative was described for decades as having nerves, or being difficult, or having a bad time, and that everyone understood not to ask further.

That is not an absence of insight. It is a person carrying two frameworks at once and trying to act inside both.

Why “just tell them” is bad advice

The instinctive suggestion is that people should educate their families. Sometimes that works. Frequently the advice underestimates what is being asked.

In households where the family unit is the primary source of identity, security, and obligation, disclosing a mental health condition is not a private medical decision. It can carry implications for how a person is regarded, what they are trusted with, and in some communities how their marriage prospects or their family’s standing are understood.

Those consequences are not imaginary and they are not evenly distributed. Telling someone their fear is just stigma, when they are the one who will live with the outcome, is not a clinical intervention. It is a person who does not bear the cost giving advice about paying it.

What we do instead is treat disclosure as a separate decision from treatment.

You do not need your family’s understanding in order to get care. You need an assessment, a plan, and, if the level of care requires it, some logistics. Family involvement in treatment is a clinical decision made with you, not a condition of entry. Some of our clients want their families deeply involved. Some choose not to involve them at all, for reasons that are entirely their own to weigh.

Separating those two questions frees people to start, which matters, because the alternative is often waiting years for a conversation that may never feel possible.

The generational split

There is a second version of this that comes up as often, and it runs the other direction.

Adults who grew up in immigrant households frequently arrive carrying a sense of obligation that makes their own suffering difficult to justify. Their parents sacrificed something substantial. They themselves have material stability their parents did not have. The internal logic is: given what was given up for me, what right do I have to be struggling?

That reasoning is genuinely coherent and it is also a very effective way to keep someone from ever seeking care. It converts a treatable condition into a question of gratitude.

We name it directly when we hear it, because naming it usually does more than arguing with it. Depression and anxiety are not distributed according to whether a person’s circumstances justify them. They are conditions with biological and psychological mechanisms, and they do not audit your family history before appearing.

What treatment actually involves, for someone who has never done this

A lot of the people we describe here have never spoken to a mental health professional. So here is what the process is, without euphemism.

An assessment is a long conversation. Symptoms, history, sleep, substance use, family, work, safety, and what you want out of this. It is not a test and there is no way to fail it. It typically ends with a recommendation about level of care.

Most people do not need intensive treatment. Weekly counseling is the right starting point for a large share of situations, and if that is what fits, we will say so.

Where we come in is further along. A mental health intensive outpatient program provides several hours of structured clinical work several days a week over eight to twelve weeks. It suits people who need substantially more contact than weekly care, often because a pattern has been running for years and has become automatic. Above it sits partial hospitalization.

Confidentiality is not a courtesy. Your participation is protected health information. It is not disclosed to an employer, a relative, or anyone else without your written authorization, regardless of who is paying the insurance premium.

Nobody is going to tell you your culture is the problem. Our clinical staff is trained in identity-affirming care, which in practice means we work with your framework rather than asking you to abandon it. Family, obligation, faith, and community are treated as facts about your life to be worked with, not obstacles to be removed.

For adults traveling to us from Irving, most stay in our transitional housing in Austin for the duration rather than driving three hours several times a week, and our case management team handles insurance and any leave documentation.

What to do if the family framework is not going to change

Some practical options, in rough order of how often they help.

Start without disclosing. You are an adult seeking medical care. That is sufficient.

Reframe it in terms the household already accepts. Sleep, stress, physical symptoms, and functioning are frequently discussable in families where “depression” is not. This is not deception. Those are real features of the condition and they are often the entry point that eventually opens the rest.

Use a physician as the bridge. In many families, a doctor carries authority that a therapist does not. A primary care visit is often the most acceptable first step and can lead to assessment, prescription, or referral.

Find one person. Not the whole family. One sibling, cousin, or friend who will know. The difference between nobody knowing and one person knowing is disproportionately large.

Be realistic about who will come around and who will not. Some relatives will surprise you. Some will not change, and building your treatment around the hope that they will is a way of postponing it indefinitely.

Give it time rather than a conversation. Families frequently accept the fact of improvement more readily than the explanation for it. Several relatives who were opposed at the start have come around after watching someone get better.

What identity-affirming care means in practice

The phrase gets used loosely, so it is worth saying what we mean by it concretely rather than as a value statement.

We do not treat your framework as the pathology. Family obligation, religious practice, community standing, and duty to parents are facts about your life. A clinician who treats them as obstacles to be argued away is asking you to choose between treatment and everything else, which is not a real choice.

We ask about them explicitly. Assessment covers who is in your family, what is expected of you, what is discussable at home and what is not, and what role faith plays if any. Not as background color. Those things shape what a workable treatment plan looks like.

We do not assume the Western default. A great deal of standard psychotherapy carries assumptions about individual autonomy as the goal, and about separation from family as a marker of health. Those assumptions are not universal and we do not apply them by default.

We are honest about our limits. Our program is small. We cannot claim clinicians matched to every background, and we would rather tell you that plainly than imply a depth of representation we do not have. If language or cultural fit is central for you, ask directly and we will give you a straight answer, including a referral elsewhere if that serves you better.

Groups are handled carefully. Being the only person in a room from your background is a real thing, and it is worth raising rather than absorbing. Our clinical staff is trained to notice it rather than waiting for someone to mention it.

Frequently asked questions

Will my family be contacted if I enter treatment? No, not without your written authorization. Family involvement is offered and discussed, never imposed. Our page for families describes how it works for clients who do want it.

Do you have clinicians who share my background? Ask on the first call and we will answer honestly rather than making a general claim. Our program is small, and we would rather tell you plainly what we can and cannot offer on this than overstate it.

What if English is not my first language, or not my parents’ first language? Raise it early. We will be direct about what we can accommodate well and where we would be stretching, because a program that cannot communicate properly with you is not a program that can treat you.

Is it disloyal to get treatment my family would not approve of? That is a question about your values rather than a clinical one, and we would not pretend to answer it for you. What we would say is that treatment is a medical decision, and that many people find the loyalty question looks different once they are better.

Can faith be part of treatment? Yes, if you want it to be. For many people religious community and practice are genuine sources of support and meaning, and treatment that ignores them is treatment that ignores something important.

What if I have already tried therapy and it did not fit? That is common, and often the issue was fit rather than therapy as a concept. It is worth saying specifically what did not work, because it changes what we would recommend.

How private is the first phone call? Entirely. Nothing from an intake conversation is shared with anyone, including an insurer beyond what a benefits check requires, without your authorization.

Handling it yourself is a reasonable instinct with a specific failure point

More than four in five adults who needed treatment and did not get it said they believed they should be able to manage it alone. That belief is usually built from a long record of managing hard things successfully, and often from watching a previous generation manage harder ones.

Where it breaks down is narrow. Effort, discipline, and endurance move most obstacles. They do not move a depressive episode or an anxiety disorder much, and applied hard enough for long enough they produce exhaustion that gets read as further personal failure.

Using a specialist for a specialist problem is not a departure from self-reliance. It is what self-reliant people do about things that do not respond to effort.

If you have been carrying something for a while, we would be glad to talk it through, with no assumption about what you disclose to anyone. Our team will assess honestly, verify your insurance, and tell you plainly whether our program for adults traveling from Irving is the right level of care. You can reach us through our contact page.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

When men talk to us about food and their bodies, they rarely use the phrase eating disorder. They talk about discipline. About cutting. About being strict in the off-season, or dialling in their macros, or needing to get their body fat down before a trip. The vocabulary is athletic and the framing is achievement. It takes a while before anyone says the quiet part, which is that it stopped being a choice some time ago.

Eating disorders in men and boys are underdiagnosed, and the reasons are not mysterious. The stereotype says these are conditions that affect teenage girls. Men internalise that, families internalise it, and so do a good number of clinicians. The result is a population that gets identified late, treated less, and studied less.

This article covers what the research shows, why male presentations often look different, and what to do if any of it sounds like you or someone you love.

What the research shows

Start with the population data, because it sets a floor. The National Institute of Mental Health reports lifetime prevalence among adolescents aged 13 to 18 at 2.7 percent overall, broken out as 3.8 percent of girls and 1.5 percent of boys. Among adults, anorexia nervosa lifetime prevalence is 0.9 percent in women and 0.3 percent in men. Those figures come from national diagnostic interviews, and by that measure eating disorders are meaningfully more common in women and girls.

That is not the whole picture, and here is where it gets more interesting.

A 2025 study by Kyle Ganson and colleagues at the University of Toronto, published in Eating Behaviors, screened boys and men across the United States and Canada and found that 21.3 percent met criteria for a probable eating disorder, with bulimia nervosa the most common probable diagnosis and anorexia nervosa the least. Among the subgroups, roughly 20 percent of men aged 18 to 24 and 18 percent of those aged 25 to 29 met criteria. Gay and bisexual men had approximately twice the odds compared with heterosexual men. Higher BMI was associated with greater odds, rising about 18 percent for each one-point increase.

We want to be careful with that number, because it is easy to misuse. Twenty-one percent is dramatically higher than NIMH’s population estimates, and the two are not measuring the same thing. Ganson’s study used screening instruments in a non-representative online sample, which identifies probable cases rather than confirming clinical diagnoses. Screening deliberately casts a wide net and will always produce higher figures than diagnostic interviews. Anyone telling you one in five men has an eating disorder is overstating what this research found.

What the study does establish is more useful than a headline. Male eating disorder symptoms are common enough in these samples to be a genuine clinical concern, they skew toward bulimic and binge-type presentations rather than the anorexia stereotype, and the risk is unevenly distributed in ways that a thinness-focused screen would miss entirely.

Alongside that, a 2023 review by Tiffany Brown and Pamela Keel in the Annual Review of Clinical Psychology documents how eating disorder research and clinical care have historically focused on girls and women, which reinforced the idea that these are a female problem. And a 2025 commentary by Hans Hoek in the International Journal of Eating Disorders notes that while recognition among males has improved, they remain underrepresented both in clinical settings and in research.

Underrepresented in research is not a minor footnote. It means that when a man does present, the evidence base a clinician draws on was largely built without him in it.

Why male presentations get missed

The goal is often not thinness

This is the single biggest reason screening fails. A meaningful share of men with disordered eating are not trying to be smaller. They are trying to be leaner, more muscular, more defined. The behaviours can be just as rigid and just as consuming, but they point in a different direction, so a clinician asking about fear of weight gain may hear a confident no and stop there.

The behaviour reads as virtue

Weighing food, training twice a day, eliminating entire food groups, and structuring social life around a regimen all attract praise in a way that other symptoms do not. Someone whose life has narrowed considerably gets told they have willpower. That feedback makes the pattern harder to question, not easier.

Exercise is the vector

For many men the compensatory behaviour is training rather than anything that looks like a classic eating disorder symptom. It is socially sanctioned, easy to explain, and almost never flagged.

Nobody asks

Men are less likely to be screened, and less likely to raise it themselves. Naming it means claiming a condition culturally coded as feminine, which is a real barrier and not a trivial one.

It arrives dressed as something else

Men often present for anxiety, low mood, insomnia, irritability, injuries that will not heal, or relationship strain. Those are the presenting problems. The eating comes up later, if at all.

The conditions underneath

That last point is where our work usually sits.

NIMH’s comorbidity data shows eating disorders overwhelmingly travel with other psychiatric conditions. More than half of adults with anorexia nervosa, nearly 95 percent of those with bulimia nervosa, and roughly 79 percent of those with binge eating disorder met criteria for at least one other core disorder, with anxiety disorders the most common across all three.

For the men we see, the entry point is almost always one of those other conditions. Someone comes in because the anxiety will not switch off, or because the low mood has taken their motivation, or because something they have carried for years has become unmanageable. The rigid relationship with food and training surfaces later, once there is enough trust for it to be mentioned without shame attached.

Asking a man to give up a coping behaviour without treating the distress it was managing rarely holds, particularly when the behaviour is also the main thing holding his self-esteem together.

How we work

Lucent is a clinician-owned outpatient mental health practice in Austin. We treat anxiety, depression, trauma, obsessive patterns, and substance use through our intensive outpatient program, our partial hospitalization program, and mental health counseling, with master’s level case management handling the practical side.

For many of the men we see, group work is the turning point. Shame does not survive contact with other people who recognise it, and a room of men who have quietly organised their lives around food and training tends to do something that individual sessions alone do not.

We will also say plainly that we do not treat compulsive exercise as a fitness problem to be optimised. If training has become the mechanism, that is a clinical matter, and the answer is not a better program.

If you are already working with a physician or another provider, we coordinate with them rather than asking you to start over.

If you are worried about a man in your life

The instinct is usually to comment on the behaviour. Try not to lead there.

Comments about food, weight, appearance, or physique tend to reinforce the framework the disorder already runs on, even when they come from love and even when they are complimentary. Praising someone’s discipline or noticing how lean they are looking can land as encouragement to continue.

What tends to help more is naming what you have noticed about their life rather than their body. That they seem more anxious. That they have stopped coming to things. That meals out have become difficult. That the training schedule has taken over. Those observations are harder to argue with and they do not put anyone on trial.

Then let it be a conversation rather than a confrontation, and expect it to take more than one attempt. Our What to Expect for Families page covers what involvement looks like in practice.

Frequently asked questions

Can men have anorexia? Yes. It is less common than in women, with NIMH putting adult lifetime prevalence at 0.3 percent in men against 0.9 percent in women, but less common is not rare, and men with anorexia are often identified later and at greater medical severity because nobody was looking.

Is muscle dysmorphia an eating disorder? Muscle dysmorphia is classified as a specifier of body dysmorphic disorder rather than an eating disorder, but the two frequently overlap and the eating behaviours involved can be seriously disordered. It is worth assessing either way.

What if I am not underweight and my bloodwork is normal? Neither rules anything out. Most people with eating disorders are not medically underweight, and bulimic and binge-type presentations, which appear to be the more common male pattern in the screening research, are not characterised by low weight at all.

Where is the line between being disciplined about training and having a problem? There is no single threshold, but useful questions are how much mental space it occupies, what happens emotionally when the routine is disrupted, and whether it has cost you relationships, work, or sleep. If the honest answer to the last one is yes, the label matters less than the conversation.

Are eating disorders in gay and bisexual men more common? The Ganson study found roughly twice the odds compared with heterosexual men. That is one screening study, so treat it as a signal rather than a settled figure, but it is consistent with the broader literature on minority stress.

Do I have to call it an eating disorder to get help? No. You do not need a diagnosis or the right vocabulary to have an assessment. Plenty of the men we see never use the term.

What we would want you to take from this

The research picture is genuinely mixed, and we would rather show you that than tidy it up. Population surveys put male eating disorders in the low single digits. Screening studies in specific samples put symptoms far higher. Both are true measurements of different things, and the honest summary is that we do not know the real figure as precisely as we would like, largely because men have been left out of this research for decades.

What is not ambiguous is the direction of the error. Men get identified late, or not at all, because the screening tools, the stereotype, and the cultural script all point away from them.

If food, your body, or your training has taken up more of your life than you want it to, that is reason enough to talk to someone. You do not need to be in crisis and you do not need to be certain.

Reach out

Our team is glad to talk through where you are, with no pressure and no assumptions. If you have been looking for eating disorder treatment in Austin, TX and are not sure where to start, an assessment is the place to begin.

For eating disorder support and referrals, the National Alliance for Eating Disorders runs a free helpline staffed by licensed therapists at 1-866-662-1235, Monday through Friday, 9:00 a.m. to 7:00 p.m. Eastern. If you or someone you love is in crisis, the 988 Suicide and Crisis Lifeline is available 24 hours a day by call or text at 988.

You can contact our team or call 512-588-3899.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas

Authored by the Clinical Team at Lucent Recovery and Wellness
Reviewed by Chris Hudson, MA, LPC, LCDC

In November 2024 the National Center for Health Statistics published National Health Statistics Report 213, examining symptoms of anxiety and depression among U.S. adults using the GAD-7 and PHQ-8 screening instruments. It found that about one in five adults experienced any symptoms of anxiety, 18.2 percent, or any symptoms of depression, 21.4 percent, in a two-week window. Both figures had risen significantly since 2019, and the increases showed up across nearly every subgroup examined.

More recently, the 2025 National Survey on Drug Use and Health, released by SAMHSA in July 2026, found that 6.6 percent of adults, roughly 17.5 million people, had moderate or severe anxiety symptoms in the previous two weeks.

Neither of those datasets breaks out results by work schedule. We wish they did, because the single most consistent thing we hear from adults in shift-based work is not a mental health complaint at all. It is a sleep complaint. And by the time someone calls us, the sleep problem and the mood problem have usually stopped being separable.

Why sleep is a clinical issue, not a lifestyle one

There is a tendency to file sleep under wellness, alongside hydration and stretching. That framing badly undersells it.

Sleep is where emotional memory gets processed and where the regulatory systems that let a person tolerate stress get restored. When it goes, several things follow with some predictability.

Emotional regulation degrades first. The gap between something happening and reacting to it narrows. People describe a shorter fuse, more tearfulness, or a general sense of being raw.

Threat sensitivity rises. A sleep-deprived nervous system reads ambiguous situations as more dangerous than a rested one does. This is a substantial contributor to anxiety that seems to have appeared from nowhere.

Cognitive capacity drops in ways that feel like personal failure. Forgetting things, losing words, making errors. People conclude something is wrong with them rather than with their sleep.

Mood follows. Persistent sleep disruption is both a symptom of depressive and anxiety disorders and a risk factor for developing them. The relationship runs in both directions, which is what makes it a loop rather than a symptom.

The clinically important consequence is this: someone sleeping four broken hours a night is being asked to do therapeutic work with impaired equipment. Cognitive behavioral therapy asks you to notice a thought, tolerate discomfort, and try something different. Those are exactly the capacities that sleep loss takes away.

The Garland context

We serve adults across the Dallas-Fort Worth metroplex, and Garland has a schedule profile worth naming directly.

It is a working city of roughly a quarter million people with a substantial manufacturing and distribution base, a large service sector, healthcare employment, and long commutes into Dallas for many residents. That mix produces a lot of second shift, third shift, rotating schedules, split schedules, and households where two adults work opposite hours specifically so somebody is home with the kids.

The consequences stack in a particular way.

Rotating schedules are harder on the body than a fixed unusual schedule. A person on permanent nights can adapt to some degree. A person rotating every two weeks never finishes adapting to anything.

Weekend recovery does not work the way people hope. Sleeping until two on Saturday shifts the internal clock further, which makes Monday worse. It is a rational response that compounds the problem.

Daytime sleep is lower quality almost regardless of what someone does. Light, noise, and household activity all interfere, and the body’s own rhythm is arguing against it.

And critically, almost all outpatient mental health care in this country operates during the hours a shift worker is either working or trying to sleep. The people whose schedules most degrade their sleep are the people least able to access care about it.

What can actually be done while the schedule stays the same

Most people cannot simply change their job, so advice that begins there is useless. Here is what is available inside a fixed constraint.

Anchor the wake time, not the bedtime. Consistency of waking is the more powerful lever, and it is more controllable. Even on days off, keeping within an hour or two of your usual wake time preserves far more than sleeping in gains.

Control light deliberately. Bright light exposure at the start of your active period and darkness before your sleep period does most of the circadian work. For night shift workers this often means blackout coverage and, sometimes, sunglasses on the drive home.

Protect the sleep window like a shift. Household members frequently do not treat daytime sleep as real sleep. Making it explicit and non-negotiable is one of the highest-return conversations available.

Move the alcohol out of the sleep routine. Alcohol shortens sleep latency and degrades everything after. This is one of the most common sleep aids in shift-work households and one of the most counterproductive.

Time caffeine against your shift, not the clock. Late-shift caffeine has the same effect as late-evening caffeine for a day worker.

Use physical activity as an adjunct. A March 2026 umbrella review in the British Journal of Sports Medicine synthesized meta-analytic evidence on exercise for depression and anxiety symptoms, and a January 2026 Cochrane update on exercise for depression found it may be moderately effective compared with no therapy, on low-certainty evidence. That is a real, replicated, modest effect. Not a treatment on its own. Worth doing anyway, and worth timing earlier in your active period rather than immediately before sleep.

If those things change nothing after a genuine attempt, that is useful information. It suggests the sleep problem is downstream of a mood or anxiety disorder rather than upstream of it, and the target should change accordingly.

When it has gone past sleep hygiene

There is a point where advice about light exposure stops being the right conversation.

Some markers: waking consistently at three or four in the morning unable to return to sleep, which is a classic depressive pattern rather than a scheduling one. Sleeping adequate hours and waking unrefreshed for months. Dread on waking. Anhedonia, where things that used to produce pleasure produce nothing. Anxiety that persists on days off and during vacations.

At that stage the useful question is level of care. Weekly counseling helps many people and is the sensible starting point if you have not tried it.

Where an intensive outpatient program becomes worth considering is when the pattern has been running for years, when weekly care has plateaued, or when sleep, mood, and alcohol have merged into one thing that cannot be pulled apart from inside.

We will be direct about the tension: an IOP runs during the day, several days a week, over eight to twelve weeks. It does not layer onto a shift schedule. Most clients traveling to us from North Texas step back from work for the duration, and our case management team handles leave documentation.

There is one genuine advantage for this specific problem. Clients staying in our transitional housing in Austin get several weeks of a consistent schedule in a quiet, substance-free environment, which is frequently the first stable sleep they have had in years. For a sleep-and-mood loop, removing the schedule that maintains it is not a side benefit. It is a large part of the intervention. Programming also includes movement and outdoor time, which supports the same target.

What to rule out before assuming it is psychological

Before concluding that broken sleep is a mood problem, a few medical contributors are worth excluding, because they are common, treatable, and frequently missed in people who work unusual hours.

Obstructive sleep apnea. Underdiagnosed generally and substantially underdiagnosed in people who sleep during the day, since partners are less likely to observe it. Symptoms include loud snoring, waking unrefreshed regardless of duration, morning headaches, and daytime sleepiness that feels different from ordinary tiredness. It is strongly associated with depressive symptoms, and treating it sometimes resolves what looked like a mood disorder.

Thyroid dysfunction. A simple blood test. Both directions produce symptoms that overlap heavily with depression and anxiety.

Iron deficiency and anemia. Fatigue and low mood, and easily checked.

Vitamin D deficiency. Common in people who work nights and rarely see daylight. The evidence linking supplementation to mood improvement is mixed, but deficiency is worth knowing about on its own terms.

Medication side effects. Several commonly prescribed medications affect sleep or mood. Worth reviewing with a prescriber rather than assuming.

Restless legs syndrome. Often overlooked, and it fragments sleep in a way that people do not always connect to how they feel during the day.

A primary care visit covering these is usually the most efficient first step available to someone with a difficult schedule, and it is the appointment most likely to be schedulable. It also strengthens the picture if you do eventually pursue mental health treatment, because it removes ambiguity about what is driving what.

If you can only do one thing from this article, make it the primary care appointment. It is the shortest, cheapest, and most schedulable step available, it can rule out several treatable physical contributors, and it opens a route to a referral if the answer turns out to be psychological after all.

Frequently asked questions

Is shift work itself causing my depression? Shift work is associated with poorer sleep and higher rates of mood and anxiety symptoms, but association is not the same as cause for any individual. Plenty of people work shifts without developing a mood disorder. It is best understood as a significant stressor rather than a diagnosis.

Should I try sleep medication? That is a conversation with a physician. Some options are appropriate short term. Several commonly used ones lose effectiveness or create dependence with extended use, so it is worth having the conversation properly rather than reaching for what is on a shelf.

Will fixing my sleep fix my mood? Sometimes substantially. Sometimes partially. If sleep repairs and mood does not follow within several weeks, that usually indicates a mood disorder that needs treating in its own right.

Can I do a program if I work nights? Our programming runs during the day, so most clients step back for the duration. We would rather say that plainly than have you enroll and find out.

How long does it take for sleep to reset? It varies, and for people in a structured environment we typically see meaningful change within the first two to three weeks. That is an observation from our program, not a guarantee.

What if my whole household runs on opposite schedules? That is common, and it is worth treating as a shared logistical problem rather than an individual one. Our page for families covers how we involve household members.

Is this something a primary care doctor can help with? Often yes, and they are frequently the most schedulable clinician in a shift worker’s life. A physician can assess, rule out contributors like sleep apnea or thyroid problems, prescribe, and refer.

The loop is the diagnosis

About one in five American adults reports symptoms of anxiety or depression in any given two-week window, and those numbers have been climbing since before 2019. None of the national datasets tell us how much of that sits with people whose schedules make ordinary sleep impossible, but the clinical picture in front of us is consistent.

If you are in that loop, the thing worth knowing is that it is not a character problem and it is not a willpower problem. It is a physiological cycle with a documented mechanism, and cycles can be interrupted. Sometimes with schedule and light and reducing alcohol. Sometimes that is not enough and it needs actual treatment.

Either way, it is worth finding out which. We would be glad to talk it through. Our team will assess honestly, verify your insurance, and tell you plainly whether our program for adults traveling from Garland is the right fit or whether something closer to home would serve you better. You can reach us through our contact page.

Healing and recovery at Lucent Recovery and Wellness

Reviewed by Chris Hudson, LPC

Founder & Executive Director – Lucent Recovery and Wellness, Austin, TX (2020–Present)
Leads clinical programs and develops innovative therapeutic approaches integrating experiential and creative therapies.

Board Member – Reklaimed, Austin, TX
Supports recovery-focused nonprofit initiatives fostering community and creative skill-building.

Clinical Leadership Roles – South Meadows Recovery, Inc.
Held leadership positions overseeing program development, clinical operations, and organizational management.

EDUCATION & CREDENTIALS

  • M.A., Clinical Mental Health Counseling – Seminary of the Southwest (2021)
  • B.A., Studio Art – Lewis & Clark College (2004)
  • Licensed Professional Counselor (LPC), Texas
  • Licensed Chemical Dependency Counselor (LCDC), Texas









